
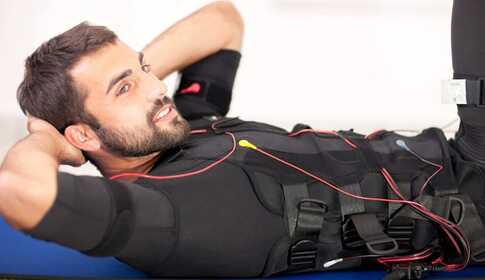

 What is the difference between WB-EMS and NMES?
I discussed the foundations of EMS technology in the EMS cornerstone article and the article on the theoretical foundations of muscle stimulation. Sports use is explained in detail in EMS for sport, while rehabilitation use is covered in the NMES rehabilitation and sport article.
 Key point
WB-EMS uses special clothing containing electrodes sewn into the fabric and stimulates 10–12 major muscle groups at the same time – typically during a 20-minute, instructor-supervised studio workout. NMES is a portable home-use device that targets one or a few muscle groups at a time with self-adhesive electrodes. According to the 2021 Kemmler meta-analysis (PMID 33716787), WB-EMS significantly increases muscle mass and strength, but body fat does not decrease on its own. The 2022 Bloeckl study (PMID 35812334) also found it safe in frail older people. Both methods complement – but do not replace – a conventional exercise programme.
 Precise definition of the two methods
Although the basic electrical pulse is similar in both methods, their clinical positioning and method of use are fundamentally different:
WB-EMS uses special clothing containing a wired electrode system (vest, trousers, wrist and ankle straps), covering 10–12 major muscle groups at the same time. The user receives stimulation through wet electrodes while performing light, dynamic movements (squats, step-ups, trunk bracing, etc.). A “session” typically lasts 20 minutes as part of an instructor-supervised studio workout, 1–2 times a week. The method grew strongly in Europe (Germany and Italy) during the 2010s and is also available in fitness studios in Hungary.
NMES is a portable device that can also be used at home. It uses self-adhesive electrodes through 2–4 channels to target one muscle or muscle group at a time. Typical uses include sport-specific strength training (Globus Cycling Pro for runners, Runner Pro, etc.), post-operative rehabilitation (Rehalito, Myolito) and the management of age-related muscle loss (sarcopenia). A session lasts 15–30 minutes per muscle group, 3–5 times a week. Only a limited area can be stimulated at one time – typically one or two muscle groups.
Both WB-EMS and NMES use a biphasic square-wave electrical pulse. The polarity of the current reverses many times per second, preventing electrochemical build-up under the skin and precisely directing stimulation of the motor nerve fibres in the muscle. The biochemical process of muscle contraction is the same with both methods – the same ion channels open, and calcium moves through the muscle fibres in the same way as when the command comes from the brain. More details are available in the article on the theoretical foundations.
Detailed comparison – 10 dimensions
| Aspect | WB-EMS | NMES |
|---|---|---|
| Coverage | 10–12 major muscle groups at the same time | 1–2 muscle groups (2-channel), max 4 (4-channel) |
| Session length | 20 minutes (typically) | 15–30 minutes / muscle group |
| Weekly frequency | 1–2 sessions (more is not recommended) | 3–5 sessions (depending on the goal) |
| Location | Studio, under instructor supervision | At home, independently or under physiotherapist supervision |
| Device access | Subscription-based (studio service) | One-off purchase (your own device) |
| Cost | ~12 000–40 000 Ft / 20 minutes; a 10-session pass is close to an average salary | ~50 000 Ft (entry level) – ~200 000 Ft (PRO), one-off |
| Typical protocol | 85 Hz, 350 μs, 4s/4s stimulation/rest, medium-high intensity (Kemmler 2020) | Variable 1–80 Hz, 200–400 μs, targeted programmes |
| Sport-specific protocol | General functional | Yes — Globus Cycling/Runner/Soccer/Triathlon Pro |
| Sarcopenia / older age | Yes, with an instructor (Yang 2022, Bloeckl 2022) | Yes, at home (Xu 2025) |
| Safety profile | Requires greater caution (risk of rhabdomyolysis at extreme intensity) | Low — minimal side effects within the approved parameter range |
 Safety – what should you know about WB-EMS?
WB-EMS is effective, but recent literature specifically calls for increased caution regarding safety. A 2019 BMJ review by Stöllberger and Finsterer (PMID 31908835) listed seven documented cases of rhabdomyolysis after WB-EMS training – most were linked to unsupervised use or excessively high intensity. The reason is that WB-EMS triggers strong contractions throughout the entire musculature at the same time, which can cause a significant rise in creatine kinase (CK) even in healthy people. Recent clinical observations include:
- Kemmler 2020 (PMID 32612355): In older men with sarcopenia, the combination of WB-EMS and high protein intake produced a mild but significant rise in CK (140 U/L); severe rhabdomyolysis did NOT occur. Kidney function (eGFR) did not worsen. Mild increases were measured in cardiac markers (hs-troponin T, CK-MB), but this did NOT increase the risk of heart failure.
- Bloeckl 2022 (PMID 35812334): An 8-week WB-EMS pilot in 7 frail older people (mean age 81) found that the CK increase was modest and temporary; none of the participants reached the critical threshold of 5000 U/L. There were no signs of rhabdomyolysis. Significant improvements were seen in the SPPB score, hand-grip strength and quadriceps strength.
- Stöllberger 2019: Proposed screening protocol: before starting WB-EMS, medical consultation to rule out risk factors for rhabdomyolysis (statin treatment, genetic susceptibility to malignant hyperthermia, previous rhabdomyolysis, severe kidney disease).
Compared with NMES, WB-EMS uses a higher intensity threshold – which is why it can be effective in 20-minute sessions, but also why it is more sensitive to parameter settings. The basic rules for safe WB-EMS use are:
- First session at a deliberately low intensity (below 30–40% of maximum).
- 48–72 hours of recovery between two workouts.
- Gradual progression over several weeks – never increase in large steps.
- Drink plenty of fluids after the session.
- New symptoms (dark urine, severe muscle pain, muscle weakness) require immediate medical assessment.
Home NMES devices operate within the approved parameter range, so the risk of rhabdomyolysis is considerably lower. According to the Beier 2024 evidence map (PMID 38339689), reports of serious adverse effects were rare in 86 WB-EMS trials – particularly when training was supervised by a suitably qualified instructor.
 For athletes – which is the more practical choice?
Sports research supports a combined, selective approach. According to the 2022 systematic review by Borzuola (PMID 35856620), the combination of NMES and voluntary contraction (NMES+) produces greater strength gains than purely passive stimulation. The 2021 Kemmler meta-analysis (PMID 33716787), however, found a significant increase in muscle mass with WB-EMS – although mainly in non-athletic adults.
When is it worth choosing WB-EMS?
- An amateur athlete with limited time who wants a full-body workout in 20-minute blocks, 1–2 times a week.
- Specifically for beginning strength training in older age, within a professionally supervised programme.
- For someone who wants to start with a studio service before investing in their own device.
When is NMES more practical?
- Sport-specific protocols are needed (Cycling Pro for cyclists, Runner Pro for runners, Triathlon Pro for triathletes – see the sport stimulator category).
- A specific muscle group (e.g. quadriceps or hamstrings) needs targeted strengthening.
- For correcting asymmetry: only one side of the body or one muscle is weaker.
- For long-term use: buying your own device offers a long service life for a one-off investment.
- For rehabilitation: targeted programmes on the Globus Genesy 600 or a similar premium PRO device after ACL or TKA surgery.
According to modern literature, the two methods are NOT competitors, but serve different application contexts. The 2022 Qin RCT (PMID 36159315) found that the muscle-strengthening effect of WB-EMS was comparable to conventional weight training – so neither method “outperforms” the other; they simply work within different logistical frameworks.
Rehabilitation: targeted NMES or whole-body WB-EMS?
In rehabilitation after surgery or injury, targeted NMES is generally the more practical choice because:
- It can focus precisely on the injured muscle group (e.g. the quadriceps after ACL reconstruction) – there is no need to stimulate the whole body.
- The doctor or physiotherapist can clearly set the programme parameters for the current phase.
- It can be used at home every day – there is no need to go to a studio for every session.
- High intensity affects only the treated muscle and does not overload the surrounding tissues.
In a rehabilitation context, WB-EMS may have a complementary role, typically in the post-acute phase (6–12 weeks after surgery) and only with a trained instructor. More details: EMS rehabilitation article and muscle stimulation after surgery.
Older age and sarcopenia – both methods can help
Recent meta-analyses support both methods in the management of age-related muscle loss (sarcopenia) and sarcopenic obesity:
- According to the 2022 meta-analysis by Yang et al. (PMID 35798137), the combination of WB-EMS and protein supplementation reduces body-fat percentage and waist circumference and increases the skeletal-muscle index in middle-aged and older people with sarcopenic obesity.
- The 2025 Xu meta-analysis (PMID 40362811) confirms the same with a complex programme combining NMES, exercise and nutrition.
- The 2022 Bloeckl pilot (PMID 35812334) found that WB-EMS can be used safely in frail older people with appropriate screening and instructor supervision.
Here, the choice is a matter of access and comfort: if there is a WB-EMS studio nearby and the patient moves well, a whole-body workout once or twice a week may be beneficial. If the patient has limited mobility or prefers to train at home, an entry-level NMES device (e.g. Myolito or Rehalito) may be more practical. In both cases, it should be combined with regular exercise and adequate protein intake.
 Costs and access
The cost structures of the two methods are fundamentally different – this often determines the final decision.
| Cost item | WB-EMS | NMES |
|---|---|---|
| Entry price | ~12 000–40 000 Ft / 20 minutes | ~50 000 Ft (Myolito) – one-off purchase |
| 10-session package | ~120 000–400 000 Ft | not applicable (own device) |
| Mid-range device | — | ~100 000–160 000 Ft (Globus Elite 150 / Cycling Pro / Runner Pro) |
| One-off PRO device | — | ~250 000–330 000 Ft (Globus Genesy 600 / 1500) |
| Ongoing cost | Monthly pass or pay-as-you-go fee | Electrode replacement only (~10 000 Ft/3-6 months) |
In my experience, the price of a 10-session WB-EMS pass is close to an average salary in Hungary. At this point, it is worth considering that a quality NMES device costs far less than an intensive WB-EMS course and can be used for years. The advantage of WB-EMS is the studio experience and instructor feedback; the advantage of NMES is flexible, everyday access at home.
If you want NMES at home – which device should you choose?
The Medimarket NMES portfolio serves several types of users. Here are a few orientation points:
| Device | Positioning | Who is it for? |
|---|---|---|
| Myolito | Entry-level EMS (HOME) | Beginners, focus on one muscle group |
| Globus Elite 150 | 4-channel mid-range | Regular home training + EMS |
| Globus Cycling Pro / Runner Pro / Soccer Pro / Triathlon Pro | Sport-specific 4-channel | Cyclists / runners / footballers / triathletes |
| Globus The Champion | Premium multifunctional sports device | Athletes active in several sports |
| Globus Genesy 600 / Genesy 1500 | Multifunctional PRO | For complex rehabilitation needs |
Devices dedicated to athletes: sport stimulator category. Full EMS portfolio: muscle stimulator category.
 When should neither method be used?
Both methods are generally well tolerated, but use is not recommended or requires increased medical supervision in the following situations. Full list: electrotherapy contraindications. Applies to both methods:
- Implanted electronic device (pacemaker, ICD, nerve stimulator) – NOT without specialist (cardiologist) approval!
- Acute vascular inflammation or deep-vein thrombosis
- Active or unknown tumour in the treated area
- Epilepsy, severe peripheral neuropathy (reduced sensation)
- Acute fever, infectious condition
- Skin inflammation or wounds in the treatment area
- Pregnancy – particularly over the lower abdomen and lumbar area
- Anterior triangle of the neck (carotid line) – no electrodes
- Severe kidney disease (particularly because of the risk of rhabdomyolysis with WB-EMS)
- Statin treatment or previous rhabdomyolysis – medical consultation before WB-EMS
In Hungary, NMES devices and WB-EMS equipment are CE/MDR-certified medical devices, but NMES cannot be prescribed.
 Summary – what should you remember?
- WB-EMS: 10–12 muscle groups at once, a 20-minute studio workout with an instructor, 1–2 times a week.
- NMES: targeted home stimulation of 1–2 muscle groups, 15–30 minutes per muscle group, 3–5 times a week.
- Both methods use the same biphasic square-wave pulse – the application logistics differ.
- Clinical evidence from 2020 onwards: both can support increases in muscle mass and strength (Kemmler 2021, Borzuola 2022, Bloeckl 2022, Qin 2022, Yang 2022, Xu 2025).
- Neither method produces meaningful body-fat reduction on its own – a combination of exercise and nutrition is needed.
- Safety: rhabdomyolysis screening is recommended for WB-EMS (Stöllberger 2019); home NMES carries minimal risk within the approved parameter range.
- Cost: WB-EMS is subscription-based (10 sessions ≈ an average salary); NMES is a one-off purchase (50 000–330 000 Ft range).
Multifunctional sports choice: Globus The Champion. Mid-range BEAUTY/HOME: Globus Activa 700. Entry-level home NMES: Myolito. Sport-specific: sport stimulator category.
Frequently asked questions
Studios often advertise this in their marketing. The clinical evidence currently available is more nuanced: according to the 2022 Qin RCT (PMID 36159315), a 6-week WB-EMS programme produced similar gains in muscle strength to conventional weight training in upper-limb flexor strength – so the level of muscle loading was comparable. However, WB-EMS does NOT replace cardiovascular training, movement patterns that develop coordination or sport-specific technical exercises. A quantitative claim such as “equal to 90 minutes” is unfounded – it is better viewed as a complement, not a replacement.
WB-EMS is safe when the parameters are selected correctly and use is supervised, but the 2019 Stöllberger BMJ review (PMID 31908835) listed seven documented cases of rhabdomyolysis after WB-EMS training. Rhabdomyolysis is substantial damage to muscle fibres that can lead to impaired kidney function; it is characterised by dark urine, muscle pain and muscle weakness. Because WB-EMS stimulates the whole body at once, the muscle load can be considerable even when the user feels little. Prevention: low intensity for the first session, gradual progression, 48–72 hours of recovery and plenty of fluids. If you take statins, have had rhabdomyolysis before or have severe kidney disease, do NOT start WB-EMS without medical approval.
Yes, under the supervision of a suitably qualified instructor. The 2022 Bloeckl pilot (PMID 35812334) ran an 8-week WB-EMS programme in 7 frail older participants (mean age 81); the CK increase was modest and temporary, no rhabdomyolysis occurred, and there were significant improvements in the SPPB score and hand-grip strength. The 2020 Kemmler study (PMID 32612355) also found the combination of WB-EMS and protein to be safe in older men with sarcopenia. The key point is medical consultation before starting the programme and supervision by a trained instructor during the sessions.
Not on its own. According to the 2021 Kemmler meta-analysis (PMID 33716787, 16 RCTs, n=897), WB-EMS significantly increases muscle mass and strength, but there was no significant change in the amount of body fat. In sarcopenic obesity, however, the 2022 Yang meta-analysis (PMID 35798137) showed that the combination of WB-EMS and high protein supplementation reduces body-fat percentage and waist circumference. Muscle stimulation is therefore a complementary tool in a multimodal weight-management programme – calorie balance and nutrition are the dominant factors.
The choice depends on four factors: (1) access – is there a WB-EMS studio nearby? (2) budget – a one-off NMES device versus recurring pass costs; (3) goal – targeted single-muscle-group treatment (NMES) or a general whole-body strength block (WB-EMS); (4) age / condition – home NMES is more convenient for a frail or mobility-limited user. Many active athletes combine the two methods: one WB-EMS whole-body foundation block per week plus 3–4 NMES sessions per week using a sport-specific protocol.
WB-EMS is NOT recommended with a pacemaker because the electrode area over the chest directly affects the implanted device. With NMES, certain protocols may be possible on muscles away from the pacemaker, with a cardiologist’s approval. The basic principle is that, with any implanted electronic device (pacemaker, ICD, nerve stimulator), electrotherapy may be started only with the express permission of the specialist who manages the implant. More details: the article on implants and electrotherapy.
Related articles
- EMS cornerstone article
- Theoretical foundations of muscle stimulation – Henneman principle
- NMES rehabilitation and sport
- EMS for sport
- EMS rehabilitation – regaining muscle strength
- EMS body shaping
- EMS in practice – electrodes, intensity and schedule
- Sport stimulator category
- Electrotherapy contraindications
- Electrotherapy and implants
 Scientific sources (2020+, with particular emphasis on WB-EMS safety)
- Kemmler W, Shojaa M, Steele J, Berger J, Fröhlich M, Schoene D, von Stengel S, Kleinöder H, Kohl M. Efficacy of Whole-Body Electromyostimulation (WB-EMS) on Body Composition and Muscle Strength in Non-athletic Adults. A Systematic Review and Meta-Analysis. Front Physiol. 2021 Feb 26;12:640657. DOI: 10.3389/fphys.2021.640657 · PMID: 33716787
- Bloeckl J, Raps S, Weineck M, Kob R, Bertsch T, Kemmler W, Schoene D. Feasibility and Safety of Whole-Body Electromyostimulation in Frail Older People – A Pilot Trial. Front Physiol. 2022 Jun 24;13:856681. DOI: 10.3389/fphys.2022.856681 · PMID: 35812334
- Kemmler W, von Stengel S, Kohl M, Rohleder N, Bertsch T, Sieber CC, Freiberger E, Kob R. Safety of a Combined WB-EMS and High-Protein Diet Intervention in Sarcopenic Obese Elderly Men. Clin Interv Aging. 2020 Jun 24;15:953-967. DOI: 10.2147/CIA.S248868 · PMID: 32612355
- Stöllberger C, Finsterer J. Side effects of and contraindications for whole-body electro-myo-stimulation: a viewpoint. BMJ Open Sport Exerc Med. 2019 Dec 17;5(1):e000619. DOI: 10.1136/bmjsem-2019-000619 · PMID: 31908835
- Borzuola R, Laudani L, Labanca L, Macaluso A. Superimposing neuromuscular electrical stimulation onto voluntary contractions to improve muscle strength and mass: A systematic review. Eur J Sport Sci. 2023;23(8):1547-1559. DOI: 10.1080/17461391.2022.2104656 · PMID: 35856620

This article provides general information and does not replace consultation with a specialist, physiotherapist or sports physician. Home or studio use of WB-EMS and NMES is recommended with a CE/MDR-certified medical device and according to the instructions for use. Before starting WB-EMS – especially in older age, in the presence of chronic disease, statin treatment or a history of rhabdomyolysis – medical consultation is required. If an implanted medical device is present, electrotherapy may be started only with the permission of the specialist managing the implant.

